


Specialty
Acute appendicitis
Doctor:
Octavio Rojas Diaz
Specialty
Gastrosurgeon / Acute Appendicitis
Address
Av. Coyoacan 715
Cp 03100 Col Del Valle CDMX
Schedule consultation
Acute Appendicitis
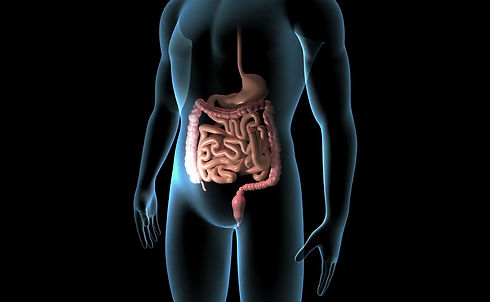
The cecal appendix, also known as the vermiform, is a finger-shaped structure found at the lower end of the right colon, near the junction with the small intestine. During the fetal and infant stage, the cecal appendix has an important immunological function, however, this function is lost over time and, although it is not essential for life, it can be removed without causing significant organic alterations.
abdominal urgency
Acute appendicitis is a common abdominal surgical emergency in emergency departments around the world. It is a progressive and acute inflammation of the cecal appendix, which if not diagnosed and treated in a timely manner, can cause perforation and fatal peritonitis.
Although it can affect anyone, it is most common in children and young adults. The main goal of treatment is to prevent appendix perforation, as this complication increases the risk of morbidity and mortality.
Obstruction is the main cause of this condition and can be caused by hard fecal matter or by an infectious process. Symptoms can range from severe, sharp abdominal pain to diffuse, progressive abdominal pain, and may be influenced by prior medical treatment.
Ultimately, obstruction of the appendix can lead to a buildup of fluid and pressure within the appendix, which can impede blood circulation and lead to necrosis and perforation. Abdominal pain is the main symptom and its form of onset and intensity can indicate the severity of the clinical picture.
around the navel
The clinical presentation of appendicitis can vary, although in most cases abdominal pain begins diffusely around the navel or in the epigastrium, followed by nausea and vomiting, poor general condition, fever, and loss of appetite.
After approximately 6 hours, the pain localized to the right iliac fossa. This picture suggests a diffuse, progressive appendiceal obstruction and generally allows the body to prepare for perforation by forming adhesions that seal the appendiceal area.
However, in other cases the onset can be abrupt, with intense pain, nausea and vomiting, but without fever or alterations in the general condition. This indicates an acute obstruction of the appendix, with more rapid inflammatory changes and the possibility of perforation in the first 6 hours, without organic preparation to prevent it. This can lead to more severe generalized peritonitis and requires immediate treatment.
It is important to take into account that not all cases of appendicitis present this typical symptomatology, since it can vary depending on factors such as the anatomical position of the appendix, the previous use of analgesics or antibiotics, or the presence of diarrhea, among others.
The diagnosis of appendicitis is clinical.
The diagnosis of appendicitis is based on clinical evaluation, physical examination, and the results of laboratory and cabinet tests. The doctor performs a careful examination of the abdomen to look for classic signs of the disease, such as pain in the McBurney region or peritoneal irritation in the right lower quadrant.
Complete blood count is a very useful tool, since leukocytosis and a shift to the left are highly suggestive signs of acute appendicitis. It is important to rule out other differential diagnoses, especially in women of childbearing age, and complement with imaging studies, such as simple abdominal x-rays, pelvic ultrasound, or abdominal tomography.
It is vital to make a timely diagnosis and perform the operation immediately, since the perforation of the appendix can lead to serious complications such as peritonitis.
Unfortunately, in the third millennium, the delay in diagnosis continues to be one of the main causes of complications in acute appendicitis. Appendectomy, which consists of the surgical removal of the appendix, remains the only effective treatment for this pathology.
Currently, thanks to laparoscopic or endoscopic surgery, the surgical procedure is simpler and less invasive, which translates into faster recovery and excellent cosmetic results.
Theme Posts
By Doctor Octavio Rojas Díaz Gastrosurgeon in CDMX
-
ACUTE APPENDICITIS AT THE NAVAL MEDICAL CENTER. NAVAL HEALTH JOURNAL 1993 VI 7:9
-
ABDOMINAL SEPSIS 3 YEARS EXPERIENCE AT THE NAVAL MEDICAL CENTER. NAVAL HEALTH JOURNAL 1993 VI 14:18
-
CURRENT STATUS OF BASIC AND ADVANCED LAPAROSCOPIC SURGERY IN 653 CASES OF A SURGICAL GROUP IN MEXICO. INTERNATIONAL MEDICAL RESEARCH 1994 21:4:171-178.
-
USEFULNESS OF LAPAROSCOPY IN SUSPECTED ACUTE ABDOMEN: INITIAL REPORT. IBERO-LATIN AMERICAN JOURNAL OF INTENSIVE CARE 1996 V 3:126--30.
-
RESOLUTION OF SIGMOID VOLVULUS BY LAPAROSCOPY. REPORT OF A PATIENT. SURGEON GENERAL 19:1:1997.
-
THE EFFICACY OF LAPAROSCOPY IN DIAGNOSIS AND TREATMENT OF PERITONITIS. EXPERIENCE IN 107 CASES IN MEXICO CITY. SURG. ENDOC 1997 11:366-370
-
Analysis of the complications of acute appendicitis. Ibero-Latin American Review of Intensive Care 1998 7(4)125-8 A
-
INTRA-ABDOMINAL SEPSIS. Ibero-Latin American Review of Intensive Care 1998 7(4)129-32
-
LAPAROSCOPIC APPENDICECTOMY Rev Iberolatinoamericana de cuidados intensivos 1999 8(4)99-192.A
-
LAPAROSCOPIC MANAGEMENT OF ACUTE PERFORATION OF THE DIGESTIVE TUBE. Ibero-Latin American Review of Intensive Care 1999 8(2)38-40
-
BOOKS
-
LAPAROSCOPY AS A DIAGNOSTIC AND THERAPEUTIC METHOD IN PERITONITIS. LAPAROSCOPIC SURGERY. IN CUETO, WEBER, INTERAMERICANA.McGRAW-HILL 1994 P:181-83.
-
POSTOPERATIVE CARE IN LAPAROSCOPIC SURGERY OF ABDOMINAL EMERGENCIES IN C. BALLESTA, THE POSTOPERATIVE IN SURGICAL LAPAROSCOPY, VIDEO MEDICA BARCELONA SPAIN 1996.


Schedule a consultationhere
